False-Positive Amphetamine Urine Screens: What Lawyers Should Request
THE OKOROCHA FIRM*
Scientific and toxicology content on this site was written by non-toxicologist marketing staff at Connectica, LLC. It has not been verified for accuracy by a trained forensic toxicologist. Read the full Content Disclaimer.
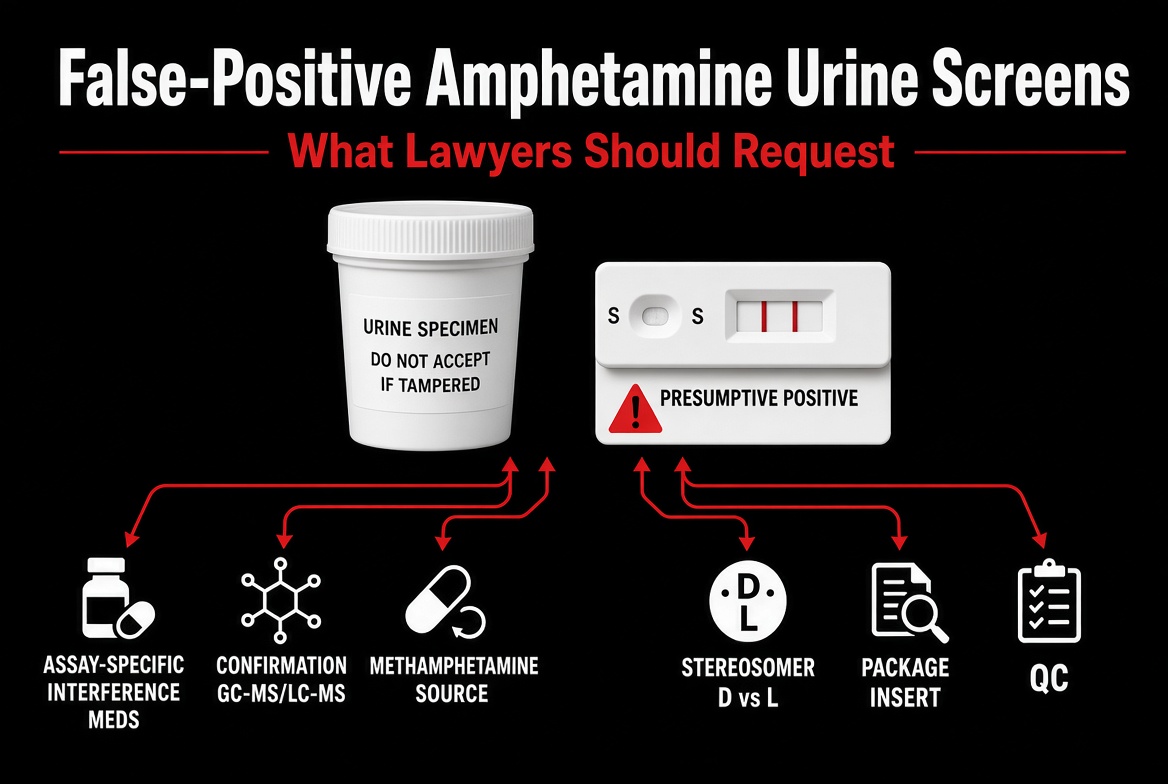
A presumptive amphetamine result can affect a criminal case, employment dispute, professional-license matter, probation proceeding, or other contested decision. But the word positive does not answer every scientific or legal question. The records must show what specimen was tested, which assay was used, what the assay was designed to recognize, and whether a chemically specific confirmation followed.
Start with the distinction between screening and confirmation
Many initial urine drug screens are immunoassays. They use antibodies to detect a target drug class or a structurally related compound. Their speed makes them useful for triage, but their response can be affected by assay design, cutoff, cross-reactivity, and the particular specimen.
A screening result is therefore ordinarily treated as presumptive. Confirmation by gas or liquid chromatography coupled with mass spectrometry addresses a different question with greater chemical specificity. Counsel should determine whether confirmation was performed, which analytes were reported, and whether the laboratory retained the raw data.
Do not rely on a generic list of medications
Published reviews describe medications and other compounds that have produced unexpected amphetamine-class screening results. Those publications are useful for identifying questions, not for proving what happened in a particular specimen. Cross-reactivity may be manufacturer-specific, reagent-specific, concentration-dependent, and different across specimen matrices.
The investigation should identify the exact test platform and obtain the applicable package insert, cross-reactivity tables, validation or verification materials, cutoff, lot information, and quality-control records. The medication history should then be compared with evidence relevant to that assay. A reported medication alone does not establish interference.
Medication examples must remain assay-specific
Published reports involving mexiletine, solriamfetol, and labetalol illustrate why a medication history can identify a question without answering it. Snozek and colleagues evaluated urine from two patients taking mexiletine. The specimens were positive on four amphetamine screening platforms but negative by mass spectrometry, and spiking drug-free urine with mexiletine reproduced positive responses on the four evaluated screens. The platforms did not respond at identical concentrations.
Kumar and colleagues reported one patient prescribed solriamfetol and then tested solriamfetol in drug-free urine. The Beckman Emit II Plus Amphetamines Assay was positive at 200 and 2,000 micrograms per milliliter, negative at 0.2 and 2 micrograms per milliliter, and the evaluated triple-quadrupole mass-spectrometry method was negative at all tested concentrations. That narrow result should not be expanded into a claim that every solriamfetol prescription causes a positive screen.
Yee and Wu described false-positive amphetamine screens in three pregnant patients receiving labetalol. That case series supports asking about labetalol and the precise assay when the history and screen conflict. It does not prove interference on every platform or explain a confirmed result in another person.
These publications support a disciplined sequence: document the medication and dose, identify the exact assay and cutoff, evaluate whether the drug or a metabolite can reach a responsive concentration in that matrix, and review the definitive test. A medication name by itself cannot establish that an analytical result was false.
A methamphetamine result may raise a source question
Methamphetamine exists in stereoisomeric forms. Certain legitimate products and medications can produce methamphetamine or related metabolites, while illicit methamphetamine is commonly associated with a different isomeric pattern. A non-chiral confirmation that reports only “methamphetamine” may not resolve that source question.
When the factual history makes a legitimate source plausible, counsel should determine whether enantiomer-specific or chiral testing was performed. Isomer testing may help evaluate source, but it does not by itself establish impairment, dose, intent, or the exact time of use.
Cross-reactivity and metabolic production are different problems
A false-positive immunoassay response and a confirmed methamphetamine result with an unresolved source should not be treated as the same issue. Cross-reactivity means that another compound caused the screening antibody to respond even though a specific confirmation did not identify the reported target. Metabolic production means that the body actually formed amphetamine or methamphetamine from another administered drug. A non-chiral confirmation can correctly identify methamphetamine while leaving its d- and l-forms unresolved.
Published human studies and reviews describe benzphetamine, famprofazone, selegiline, and certain inhaler products as possible source questions under defined circumstances. Those publications do not create a generic alternative explanation for every result. Counsel should first establish actual access and use, then compare the complete metabolite pattern, concentrations, timing, and stereoisomer data with the proposed source.
Budd and Jain reported amphetamine and methamphetamine after benzphetamine administration in one volunteer. Inoue and Suzuki later described human benzphetamine and furfenorex metabolism. Oh and colleagues, and separately Yoo and colleagues, reported methamphetamine after famprofazone administration. Fitzgerald and colleagues showed why stereoisomer separation can matter after use of a nasal inhaler containing l-methamphetamine. Cody reviewed multiple metabolic precursors and the analytical problems they can create. These historical studies identify questions to investigate; they do not establish the source in an individual case.
Assay-specific evidence is stronger than a generic medication list
Reidy and colleagues found bupropion-metabolite cross-reactivity in two of four evaluated ELISA kits, illustrating that one medication can affect some assays and not others. Vorce and colleagues investigated a cluster of amphetamine immunoassay positives that were negative by the laboratory’s confirmation method and detected dimethylamylamine in most of the examined specimens. Ayala-Lopez and colleagues used electronic health records to identify possible medication-assay associations, then experimentally tested only selected pairs. Together, these studies support an assay-specific investigation, not an assumption that every listed medication will affect every test.
Urine detection is not the same as impairment
Urine is primarily an excretion matrix. A properly confirmed urine result may support prior exposure, but it generally does not measure the concentration circulating in blood at the time of an event. Hydration, urine pH, metabolism, dose pattern, collection time, and the laboratory’s reporting rules may all affect the result.
That distinction matters whenever a party uses a urine result to argue unsafe performance, intoxication, or causation. The proponent still must connect the analytical finding to the relevant time and functional question using appropriate evidence. A qualitative screen does not supply that connection by itself.
Records to request
- the original screening result and every amended report;
- specimen labels, seals, collection records, and chain of custody;
- specimen-validity results, including creatinine, specific gravity, pH, and oxidant testing when performed;
- the assay manufacturer, model, reagent lot, target class, and cutoff;
- the package insert and laboratory validation or verification materials;
- calibrators, controls, instrument output, review records, and corrective actions;
- confirmation data, including chromatograms, spectra, transitions, calculations, and reporting criteria;
- medication, over-the-counter product, supplement, and exposure history;
- chiral or isomer testing when methamphetamine source is disputed; and
- the laboratory’s standard operating procedures in effect on the testing date.
Questions for expert review
- Was the result a screening result, a confirmed result, or both?
- Did the confirmation identify the same analyte implicated by the screen?
- Was the method appropriate for the specimen and reporting purpose?
- Could a documented medication, metabolite, or legitimate product affect this exact assay?
- Would stereoisomer testing help answer a disputed source question?
- What can the urine result support about exposure, and what can it not support about timing or impairment?
- Do the chain-of-custody, quality-control, and raw analytical records support the reported conclusion?
Why early review matters
Testing issues are easier to evaluate while the specimen, raw data, instrument records, and knowledgeable witnesses remain available. A preservation request and a focused demand for the complete laboratory packet can prevent the case from being reduced to a single summary line.
When the case depends on the science, your lawyer should understand the science. The Okorocha Firm evaluates matters in which drugs, alcohol, toxicology, laboratory methods, or other scientific evidence may determine the outcome. A case-specific assessment requires the actual report, laboratory packet, timeline, medication history, and governing legal standard.
Selected scientific references
- Saitman A, Park HD, Fitzgerald RL. False-positive interferences of common urine drug screen immunoassays: a review. Journal of Analytical Toxicology. 2014;38(7):387-396. doi:10.1093/jat/bku075.
- Reisfield GM, Goldberger BA, Bertholf RL. False-positive and false-negative test results in clinical urine drug testing. Bioanalysis. 2009;1(5):937-952. doi:10.4155/bio.09.81.
- Moeller KE, Kissack JC, Atayee RS, Lee KC. Clinical interpretation of urine drug tests: what clinicians need to know about urine drug screens. Mayo Clinic Proceedings. 2017;92(5):774-796. doi:10.1016/j.mayocp.2016.12.007.
- Snozek CLH, Kaleta EJ, Jannetto PJ, et al. False-positive amphetamine results on several drug screening platforms due to mexiletine. Clinical Biochemistry. 2018;58:125-127. doi:10.1016/j.clinbiochem.2018.05.013.
- Kumar G, Auckley D, Merrick T, et al. False positive urine amphetamine immunoassay due to solriamfetol. Sleep Medicine. 2023;110:297-299. doi:10.1016/j.sleep.2023.08.031.
- Yee LM, Wu D. False-positive amphetamine toxicology screen results in three pregnant women using labetalol. Obstetrics and Gynecology. 2011;117(2 Pt 2):503-506. doi:10.1097/AOG.0b013e318206c07c.
- Smith ML, Nichols DC, Underwood P, et al. Methamphetamine and amphetamine isomer concentrations in human urine following controlled Vicks VapoInhaler administration. Journal of Analytical Toxicology. 2014;38(8):524-527. doi:10.1093/jat/bku077.
- Fitzgerald RL, Ramos JM Jr, Bogema SC, Poklis A. Resolution of methamphetamine stereoisomers in urine drug testing: urinary excretion of R(-)-methamphetamine following use of nasal inhalers. Journal of Analytical Toxicology. 1988;12(5):255-259. doi:10.1093/jat/12.5.255.
- Inoue T, Suzuki S. The metabolism of benzphetamine and furfenorex in man. Xenobiotica. 1986;16(7):691-698. doi:10.3109/00498258609043559.
- Oh ES, Hong SK, Kang GI. Plasma and urinary concentrations of methamphetamine after oral administration of famprofazone to man. Xenobiotica. 1992;22(3):377-384. doi:10.3109/00498259209046649.
- Yoo Y, Chung H, Choi H. Urinary methamphetamine concentration following famprofazone administration. Journal of Analytical Toxicology. 1994;18(5):265-268. doi:10.1093/jat/18.5.265.
- Reidy L, Walls HC, Steele BW. Crossreactivity of bupropion metabolite with enzyme-linked immunosorbent assays designed to detect amphetamine in urine. Therapeutic Drug Monitoring. 2011;33(3):366-368. doi:10.1097/FTD.0b013e3182126d08.
- Vorce SP, Holler JM, Cawrse BM, Magluilo J Jr. Dimethylamylamine: a drug causing positive immunoassay results for amphetamines. Journal of Analytical Toxicology. 2011;35(3):183-187. doi:10.1093/anatox/35.3.183.
- Ayala-Lopez N, Colby JM, Hughey JJ. Analysis of electronic health records reveals medication-related interference on point-of-care urine drug screening assays. Journal of Analytical Toxicology. 2022;46(1):99-102. doi:10.1093/jat/bkaa179.
Related scientific reading
For a device-focused discovery checklist, read Rapid Urine Drug Tests in Court: 12 Records That Matter. For a longer evidence-focused discussion, read Presumptive Urine Drug Screens: Why Confirmation Matters. For a broader distinction between detection and functional effect, see Positive Drug Test vs. Impairment.
SCIENCE. STRATEGY. TRIAL EXPERIENCE.
General informational and marketing material only. It is not legal advice, expert opinion, or a statement of scientific fact. No attorney-client or expert-client relationship is created. Full Content Disclaimer.



